
Connecticut is home to more than 7,400 residents currently living with kidney failure — a number that has grown by over 23% in the past decade. Thousands more live with chronic kidney disease (CKD), placing them at risk of progression to end-stage renal disease, a condition that is fatal without treatment. Kidney failure demands either lifelong dialysis or a transplant, both of which carry significant medical, financial, and social consequences for patients and their families.
This article draws on multi-year data from state health records, transplant center performance reports, cancer registries, and federal kidney health databases to present a comprehensive picture of kidney disease in Connecticut. It covers the prevalence and incidence of kidney failure, access to dialysis and transplantation, the performance of the state’s two transplant centers, kidney cancer burden by county, kidney disease mortality trends, and the financial hardship associated with these conditions.
The data reveal a state grappling with persistently high disease burden, inadequate transplant access, and worsening mortality trends for kidney disease — even as cancer-related kidney outcomes improve. Understanding these patterns at the statewide and county level is essential for guiding public health priorities, clinical resource allocation, and patient support policy in Connecticut.
Chronic Kidney Disease (CKD)
Chronic kidney disease is the precursor condition to kidney failure. Its prevalence in the general population reflects the future pipeline of patients at risk of progressing to end-stage renal disease, making CKD surveillance an essential component of kidney health planning.
- Adults ever diagnosed with kidney disease (CKD): 3.4%
- Connecticut rank among states (lower = less burden): 8th
- Medicare patients with CKD diagnosed: 41,980


Connecticut’s 3.4% CKD prevalence rate ranks it 8th among states, suggesting a comparatively lower burden relative to most of the country.
Kidney Failure (End-Stage Renal Disease)
Kidney failure — also called end-stage renal disease (ESRD) — is a condition in which the kidneys can no longer filter waste and fluids adequately to sustain life. Without treatment in the form of dialysis or a transplant, it is fatal. This section covers the scale of kidney failure in Connecticut, how many new cases arise each year, what drives them, and what the resulting mortality burden looks like.
Statewide Prevalence
The following table tracks the total population living with kidney failure in Connecticut across available reporting years, along with the split between those on dialysis and those living with a transplant.
| Report Year | Total Living with Kidney Failure | On Dialysis | Living with Transplant |
| 2021 | 7,031 | 4,576 | 2,455 |
| 2022 | 7,253 | 4,685 | 2,568 |
| 2023 | 7,212 | 4,581 (63.5%) | 2,631 (36.5%) |
| 2024 | 7,245 | 4,559 | 2,686 |
| 2025 | 7,269 | 4,496 | 2,773 |
| 2026 | 7,460 | 4,547 | 2,913 |
The overall kidney failure population in Connecticut has grown steadily, rising from 7,031 in 2021 to 7,460 in 2026.
Annual New Cases
More than 1,000 Connecticut residents are newly diagnosed with kidney failure every year. The list below shows the annual new case counts and the initial treatment pathway for each diagnosed cohort.
| Diagnosis Year | New Cases | Received a Transplant | Began Dialysis |
| 2018 | 1,132 | 60 | 1,072 |
| 2019 | 1,174 | 59 | 1,115 |
| 2020 | 1,070 | 43 | 1,027 |
| 2021 | 1,120 | 59 | 1,061 |
| 2022 | 1,131 | 56 | 1,075 |
| 2023 | 1,135 | 66 | 1,069 |
New kidney failure diagnoses have remained relatively consistent, ranging from 1,070 to 1,174 per year. Dialysis is overwhelmingly the first treatment for newly diagnosed patients; the number proceeding directly to transplant each year is small, ranging from 43 to 66.
Causes and Risk Factors
Kidney failure in Connecticut is driven predominantly by two chronic, largely preventable conditions. The table below shows reported cause percentages across three consecutive data years.
| Cause | 2023 Data | 2024 Data | 2025 Data |
| Diabetes | 47% | 44% | 43% |
| High blood pressure | 30% | 29% | 30% |
| Combined | 77% | 73% | 73% |
Connecticut Population-Level Risk Factors
- 9.6% of Connecticut residents have been diagnosed with diabetes
- 30.9% have high blood pressure
- 29.1% self-report as obese
Diabetes and high blood pressure together account for approximately 73–77% of all kidney failure cases in Connecticut.
Kidney Cancer
Kidney and renal pelvis cancer is tracked separately from kidney failure and CKD. This section presents statewide incidence compared to the national average, county-level data for all stages and late-stage diagnoses, and a historical breakdown of kidney cancer among Connecticut males.
Connecticut vs. National Rates (2018–2022)
Connecticut’s kidney cancer rates compared to the national average:
- Connecticut — All Cancer Sites: 476.7 per 100,000 (US: 448.6)
- Connecticut — Kidney & Renal Pelvis: 15.5 per 100,000 (US: 17.5)
- Average annual kidney & renal pelvis cancer cases in Connecticut: 724
- Recent 5-year incidence trend (Connecticut): Stable (−3.0%; confidence interval includes zero)
- Recent 5-year incidence trend (United States): Falling (−1.0%)
Connecticut’s kidney and renal pelvis cancer incidence (15.5 per 100,000) is notably below the national rate (17.5), even as the state’s overall cancer incidence exceeds the national average.
Incidence by County
All Stages (2018–2022)
Sorted from highest to lowest rate
| County | Rate per 100,000 | 95% Confidence Interval | Avg. Annual Cases | Recent 5-Year Trend |
| New London County | 17.4 | 15.4 – 19.6 | 62 | Rising (+2.3%) |
| Middlesex County | 17.3 | 14.9 – 20.0 | 43 | Rising (+13.0%) |
| New Haven County | 16.5 | 15.4 – 17.7 | 183 | Stable |
| Hartford County | 16.3 | 15.2 – 17.4 | 184 | Stable |
| Windham County | 16.0 | 13.3 – 19.2 | 25 | Stable |
| Tolland County | 13.9 | 11.6 – 16.6 | 28 | Stable |
| Litchfield County | 13.6 | 11.7 – 15.8 | 40 | Rising (+1.3%) |
| Fairfield County | 13.4 | 12.5 – 14.4 | 160 | Stable |
| Connecticut | 15.5 | 15.0 – 16.0 | 724 | Stable |
| United States | 17.5 | 17.5 – 17.6 | 70,592 | Falling (−1.0%) |
New London and Middlesex counties report the highest kidney cancer incidence rates in Connecticut, both exceeding the national average — and both showing statistically significant rising trends.
Late Stage (2018–2022)
Late-stage diagnosis indicates how often cancer is caught at an advanced stage, which is associated with worse outcomes. Counties listed from highest to lowest late-stage rate:
| County | Rate per 100,000 | 95% Confidence Interval | Avg. Annual Cases | % Diagnosed Late |
| New Haven County | 5.3 | 4.7 – 6.0 | 60 | 32.7% |
| Hartford County | 4.8 | 4.3 – 5.5 | 55 | 29.9% |
| New London County | 4.8 | 3.9 – 6.0 | 19 | 30.3% |
| Windham County | 4.6 | 3.2 – 6.4 | 7 | 29.1% |
| Middlesex County | 4.5 | 3.4 – 5.9 | 12 | 28.6% |
| Litchfield County | 3.8 | 2.9 – 5.1 | 11 | 28.5% |
| Fairfield County | 3.4 | 3.0 – 3.9 | 42 | 26.3% |
| Tolland County | 2.7 | 1.8 – 4.1 | 5 | 19.6% |
| Connecticut | 4.4 | 4.2 – 4.7 | 212 | 29.3% |
| United States | 5.0 | 5.0 – 5.0 | 20,556 | 29.1% |
Connecticut’s late-stage kidney cancer incidence rate (4.4 per 100,000) is below the US average (5.0), and the proportion of cases diagnosed late (29.3%) is nearly identical to the national proportion (29.1%).
Historical Data: Kidney Cancer Among Connecticut Males (2015)
Cancer Site Rankings
Kidney and renal pelvis cancer ranked seventh among all male cancers diagnosed in Connecticut in 2015.
| Rank | Cancer Site | Count | % of All Male Cancers |
| 1 | Prostate | 2,380 | 23.7% |
| 2 | Lung and Bronchus | 1,245 | 12.4% |
| 3 | Urinary Bladder | 876 | 8.7% |
| 4 | Colon and Rectum | 799 | 8.0% |
| 5 | Melanoma of the Skin | 530 | 5.3% |
| 6 | Non-Hodgkin Lymphoma | 526 | 5.2% |
| 7 | Kidney and Renal Pelvis | 459 | 4.6% |
| 8 | Oral Cavity and Pharynx | 390 | 3.9% |
| 9 | Pancreas | 323 | 3.2% |
| 10 | Leukemia | 312 | 3.1% |
| — | All Other Cancers | 2,190 | 21.8% |
| — | All Cancers Combined | 10,030 | 100.0% |
Potential Life-Years Lost (PLL) to Age 75
Kidney and renal pelvis cancer accounted for 608 potential life-years lost — 2.7% of the total cancer PLL burden, placing it 10th among cancer sites. Full rankings among Connecticut males (2005–2015):
| Cancer Site | Years of PLL | % of Total PLL | APC Trend |
| Lung & Bronchus | 4,628 | 20.8% | −4.1% |
| Colon & Rectum | 1,758 | 7.9% | Not significant |
| Liver & IHB | 1,713 | 7.7% | Not significant |
| Pancreas | 1,705 | 7.7% | −2.3% |
| Brain & CNS | 1,625 | 7.3% | Not significant |
| Leukemia | 1,125 | 5.1% | Not significant |
| Esophagus | 1,060 | 4.8% | Not significant |
| Prostate | 895 | 4.0% | Not significant |
| Non-Hodgkin Lymphoma | 823 | 3.7% | Not significant |
| Kidney & Renal Pelvis | 608 | 2.7% | Not significant |
| All Cancers Combined | 22,273 | 100.0% | −1.8% |
Incidence by Race and Ethnicity (2011–2015)
| Population Group | Total Cases (5-Year) | Age-Adjusted Rate per 100,000 | 95% Lower CL | 95% Upper CL |
| Total | 2,191 | 22.2 | 21.3 | 23.2 |
| Non-Hispanic White | 1,808 | 22.4 | 21.4 | 23.5 |
| Non-Hispanic Black | 171 | 21.7 | 18.4 | 25.3 |
| Hispanic | 151 | 21.1 | 17.4 | 25.3 |
Kidney and renal pelvis cancer ranked seventh among all male cancers in Connecticut in 2015, accounting for 459 cases and 4.6% of all male cancer diagnoses.
Dialysis
For patients who cannot receive a transplant, dialysis is life-sustaining care. Dialysis is life support: treating kidney failure and its comorbidities is more consuming than a full-time job, and more than 80% of dialysis patients cannot work.
- Dialysis centers in Connecticut: 44
- Connecticut residents on dialysis (national overview): 3,762
- Medicare-covered patients on dialysis: 3,701


Connecticut’s 44 dialysis centers serve thousands of patients who depend on the treatment to survive. The dialysis-dependent population has remained persistently large across all reporting years, consistently accounting for more than 60% of all kidney failure patients.
Kidney Transplants
Kidney transplantation is the preferred treatment for kidney failure, offering better survival outcomes and quality of life than dialysis. However, access is severely limited by the chronic shortage of donor organs and the capacity of transplant centers.
Waiting List and Access
Access to kidney transplants remains severely constrained in Connecticut. The table below summarizes transplant waiting list size, the fraction of patients receiving a transplant each year, total transplants performed, and the breakdown by donor type.
| Report Year | Patients on Waiting List | Annual Transplant Rate | Total Transplants | Living Donor | Deceased Donor | Change vs. ~10 Years Prior |
| 2021 | 958 | ~1 in 4 | 239 (2020) | — | — | — |
| 2022 | 933 | ~1 in 4 | 237 (2021) | 77 | 160 | +54.9% since 2011 |
| 2023 | 930 | ~1 in 4 | 259 (2022) | 83 | 176 | +61.9% since 2012 |
| 2024 | 882 | ~1 in 3 | 269 | 88 | 181 | +78% since 2013 |
| 2025 | 876 | ~1 in 4 | 222 (2024) | 81 | 141 | +39% since 2014 |
| 2026 | 987 | ~1 in 5 | 217 (2025) | 76 | 141 | +35% since 2015 |
Additional key facts:
- 39 patients died while on the kidney transplant waiting list in 2020
- Living donor transplants increased 21% compared to 2014 (2025 data) and 3% compared to 2015 (2026 data)
- Only about 1 in 5 Connecticuters on the waiting list received a transplant in 2025 — the most restrictive access rate in the reporting period
Although total transplant volume in Connecticut has risen substantially compared to a decade ago — by 35 to 78% depending on the baseline year — this growth has not kept pace with need. The waiting list grew to 987 patients in the 2026 report (the highest in the period), while the number of transplants performed dropped to 217, meaning only approximately 1 in 5 patients received a transplant that year.
Transplant Centers
Connecticut has two kidney transplant centers: Hartford Hospital (Hartford, CT) and Yale New Haven Hospital (New Haven, CT). Both are members of the National Kidney Registry (NKR). Hartford Hospital performs the higher volume of transplants.
Donor Programs
| Feature | Hartford Hospital | Yale New Haven Hospital |
| NKR Transplants — Last 12 Months | 36 | 12 |
| Prioritization — Deceased Donor | ✓ | ✓ |
| Prioritization — Living Donor | ✓ | ✓ |
| Donor Shield | ✓ | ✓ |
| NKR Remote Donation | ✓ | ✓ |
| Voucher Program | ✓ | ✓ |
| NKR Member Center | ✓ | ✓ |
| Equal Access Commitment | ✓ | ✗ |
| Donor Referral Network | ✓ | ✗ |
| Kidney for Life | ✓ | ✗ |
| Donor Care Network | ✓ | ✗ |
| Nutcracker Care Network | ✓ | ✗ |
Both centers share the core NKR infrastructure — deceased and living donor prioritization, Donor Shield, Remote Donation, the Voucher Program, and NKR membership.
Recipient Programs
Data period: April 1, 2025 – March 31, 2026
| Feature | Hartford Hospital | Yale New Haven Hospital |
| NKR Transplants (Last 12 Months) | 36 | 12 |
| NKR Living Donor Tx — Prior Year | 40 | 10 |
| Total Living Donor Tx — Prior Year | 50 | 38 |
| NKR Share of Living Donor Tx | 80% | 27% |
| Low Eplet Tx — Last 12 Months | 8 | 2 |
| Kidney for Life Participant | Yes | No |
| Patient Microsites | Yes | No |
| Microsite Center of Excellence | Yes | No |
| Non-Steroidal Protocol | Yes | No |
| Voucher Program | Yes | Yes |
| NKR Member Center | Yes | Yes |
| Equal Access Commitment | Yes | No |
Hartford Hospital leads across nearly all recipient program metrics. Eighty percent of its living donor transplants are coordinated through the NKR, compared to 27% at Yale New Haven.
Adult Outcomes
Important note: The higher a center’s transplant volume, the less likely it is to achieve 100% survival rates. Centers that accept medically complex cases are also likely to report lower survival rates.
| Metric | Hartford Hospital | Yale New Haven Hospital |
| NKR Tx — Last 12 Months | 36 | 12 |
| Living Donor Tx — Prior Year | 50 | 38 |
| LD 1-Year Graft Survival | 99% | 99% |
| LD 3-Year Graft Survival | 97% | 96% |
| LD 1-Year Patient Survival | 99% | 99% |
| LD 3-Year Patient Survival | 99% | 96% |
| DD 1-Year Graft Survival | 89% | 93% |
| DD 3-Year Graft Survival | 88% | 86% |
| DD 1-Year Patient Survival | 93% | 97% |
| DD 3-Year Patient Survival | 91% | 92% |

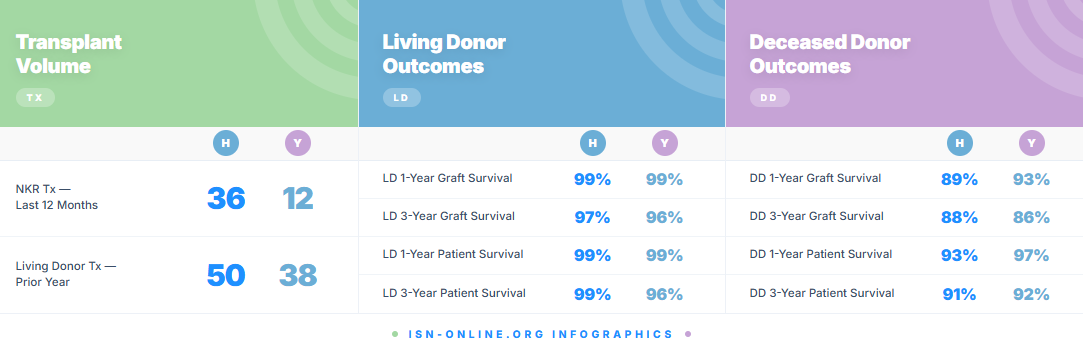
Both centers achieve excellent outcomes for living donor transplants, with identical 99% one-year graft and patient survival rates. For deceased donor transplants, Yale New Haven reports higher one-year graft survival (93% vs. 89%) and one-year patient survival (97% vs. 93%), while Hartford achieves modestly better three-year graft survival (88% vs. 86%)..
Pediatric Outcomes
Only Yale New Haven Hospital reports pediatric kidney transplant outcomes in Connecticut.
- NKR Transplants — Last 12 Months: 12
- Living Donor Tx — Prior Year: 38
- Living Donor 1-Year Graft Survival: 100%
- Living Donor 3-Year Graft Survival: 100%
- Living Donor 1-Year Patient Survival: 100%
- Living Donor 3-Year Patient Survival: 100%
- Deceased Donor 1-Year Graft Survival: 100%
- Deceased Donor 3-Year Graft Survival: 88%
- Deceased Donor 1-Year Patient Survival: 100%
- Deceased Donor 3-Year Patient Survival: 100%
Yale New Haven Hospital’s pediatric kidney transplant outcomes are exceptional, achieving 100% survival rates in nine of ten tracked categories. The only exception is deceased donor three-year graft survival at 88%, which still reflects strong performance.
Kidney Disease and Kidney Cancer Mortality Statistics
Nephritis and Nephrosis Mortality
Kidney disease deaths from nephritis and nephrosis represent the direct mortality burden of kidney failure and related disorders. Data covers 2019–2023.
| County | Death Rate per 100,000 | 95% Confidence Interval | Avg. Annual Deaths | Recent 5-Year Trend |
| New London County | 15.3 | 13.6 – 17.2 | 58 | Stable |
| New Haven County | 15.2 | 14.2 – 16.2 | 182 | Rising (+3.9%) |
| Hartford County | 14.6 | 13.6 – 15.6 | 179 | Stable |
| Tolland County | 13.1 | 10.9 – 15.7 | 25 | Stable |
| Litchfield County | 11.9 | 10.2 – 13.8 | 36 | Stable |
| Windham County | 11.4 | 9.1 – 14.1 | 18 | Stable |
| Fairfield County | 10.1 | 9.3 – 10.9 | 129 | Stable |
| Middlesex County | 9.2 | 7.6 – 11.1 | 25 | Stable |
| Connecticut | 13.0 | 12.6 – 13.5 | 652 | Rising (+2.4%) |
| United States | 13.4 | 13.3 – 13.4 | 54,332 | Stable |
Connecticut’s kidney disease death rate (13.0 per 100,000) is slightly below the national average (13.4), but the state’s trend is rising (+2.4% per year) while the national trend is stable — a concerning divergence. New Haven County is a particular area of concern: it has both one of the highest death rates in the state (15.2) and a statistically significant rising trend (+3.9% per year), with 182 average annual deaths.
Cancer Death Rates by County (2019–2023)
| County | Death Rate per 100,000 | 95% Confidence Interval | Avg. Annual Deaths | Recent 5-Year Trend |
| Windham County | 4.0 | 2.7 – 5.7 | 6 | Stable |
| New Haven County | 3.0 | 2.6 – 3.5 | 34 | Falling (−2.0%) |
| Hartford County | 2.8 | 2.4 – 3.3 | 34 | Stable |
| New London County | 2.8 | 2.1 – 3.6 | 11 | Stable |
| Tolland County | 2.5 | 1.6 – 3.8 | 5 | Falling (−2.6%) |
| Litchfield County | 2.4 | 1.7 – 3.4 | 8 | Stable |
| Fairfield County | 2.3 | 1.9 – 2.7 | 29 | Falling (−1.8%) |
| Middlesex County | 2.1 | 1.4 – 3.2 | 6 | Falling (−3.6%) |
| Connecticut | 2.7 | 2.5 – 2.9 | 132 | Falling (−1.6%) |
| United States | 3.4 | 3.4 – 3.5 | 14,378 | Falling (−1.4%) |
Connecticut’s kidney cancer death rate (2.7 per 100,000) is well below the national average (3.4), and the state’s rate is falling at a pace (−1.6% per year) comparable to the national trend (−1.4%). Middlesex County shows the steepest improvement (−3.6%), while Windham County’s rate of 4.0 — the only county exceeding the national average — warrants attention, though it is based on only 6 average annual deaths. New Haven, Fairfield, and Tolland counties also show statistically significant declining mortality trends.
Financial Burden and Patient Support
Kidney failure imposes a severe financial burden on patients, families, and the healthcare system. This section covers Medicare costs by patient type, charitable grant assistance, insurance coverage patterns, and the socioeconomic profile of affected patients.
Annual Healthcare Costs
A successful kidney transplant dramatically reduces the long-term cost of kidney failure care:
- Pre-kidney failure (CKD): $23,558 per year (average Medicare cost)
- Dialysis patient: $90,323 per year (average Medicare cost)
- Kidney transplant recipient (after first year): $25,942 per year (average Medicare cost)
A kidney transplant reduces annual Medicare costs by approximately $64,000 per patient per year compared to dialysis.
AKF Charitable Assistance
The American Kidney Fund provides grants to low-income dialysis and transplant patients to help pay for insurance premiums and health care costs not covered by insurance.
| Year | Recipients of AKF Grants | Total AKF Assistance |
| 2020 | 451 | ~$2,000,000 |
| 2021 | 392 | $1,739,838 |
| 2022 | 313 | $1,425,106 |
| 2023 | 274 | $1,053,430 |
| 2024 | 234 | $1,072,706 |
| 2025 | 218 | Not reported |
Both the number of AKF grant recipients and total charitable assistance have declined significantly since 2020 — the number of recipients fell by more than half (from 451 to 218) and total assistance dropped from approximately $2 million to just over $1 million.
Insurance Coverage of Assisted Patients
The following data shows how AKF assistance recipients were insured across four available years.
2024
- Medigap: 27.3%
- Medicare Part B: 25.0%
- Commercial Employer Group Plans (incl. COBRA): 20.1%
- Medicare Advantage: 0.6%
2023
- Medicare Part B: 44.6%
- Medigap: 23.4%
- Employer Group Health Plans (incl. COBRA): 17.2%
- Medicare Advantage: 1.4%
2022
- Medicare Part B: 40.9%
- Medigap: 27.2%
- Commercial Employer Group Plans (incl. COBRA): 17.7%
- Medicare Advantage: 1.3%
2021
- Medicare Part B: 36.8%
- Medigap: 31.1%
- Employer Group Health Plans (incl. COBRA): 18.9%
- Commercial Plans: 10.5%
- Exchange Plans: 3.4%
- Annuity: 1.5%
- Medicare Advantage: 1.2%
- Medicaid (states with premiums): 0.1%
Medicare Part B and Medigap (Medicare supplemental coverage) are consistently the most common insurance types among AKF assistance recipients in Connecticut, reflecting the predominantly Medicare-eligible population of dialysis and transplant patients.
Patient Demographics and Socioeconomic Profile
The kidney failure population in Connecticut — and particularly those requiring charitable assistance — faces compounding economic and social disadvantages.
- Dialysis patients unable to work: >80%
- Kidney failure classification: A disability
- Average annual income of AKF-assisted patients: <$25,000
- Average annual out-of-pocket costs for dialysis patients: >$10,000
- Minority patients among those AKF assists: >60% (Black: 34.7%; Hispanic / Latino: 20.9%; Native American / Asian / Pacific Islander: 5.2%)
Kidney failure is profoundly disabling: the vast majority of dialysis patients cannot maintain employment, yet they face out-of-pocket medical costs exceeding $10,000 per year on average incomes below $25,000 — a ratio that constitutes severe financial hardship. The racial and ethnic composition of patients receiving AKF assistance reflects the well-documented disproportionate burden of kidney failure in Black, Hispanic, and Native American communities, where the two primary risk factors — diabetes and high blood pressure — are also more prevalent.
Conclusion
Connecticut’s kidney disease landscape presents a picture of growing burden alongside incremental progress. The total kidney failure population has risen steadily, reaching 7,460 residents in the most recent reporting year, while the number living with a functioning transplant has grown from 2,455 to 2,913 over the same period — a sign that transplant access has improved modestly. Both transplant centers achieve strong clinical outcomes, with Hartford Hospital emerging as a more comprehensive program across donor and recipient services, and Yale New Haven Hospital providing the state’s only pediatric kidney transplant service with exceptional survival results.
Several trends demand urgent attention. The proportion of patients on the waiting list who receive a transplant has declined to approximately 1 in 5, even as the waiting list itself has grown to nearly 1,000 patients. Kidney disease mortality from nephritis and nephrosis is rising statewide at a pace that outpaces the stable national trend, with New Haven County registering a statistically significant increase of nearly 4% per year. Financial hardship remains pervasive: dialysis patients face out-of-pocket costs exceeding $10,000 per year on average incomes below $25,000, and more than 80% cannot work. Minority communities — Black, Hispanic, and Native American — continue to bear a disproportionate share of the disease burden.
Prevention and access are the two levers most likely to change outcomes at scale. Diabetes and high blood pressure together account for approximately three-quarters of all kidney failure cases in Connecticut, and both are closely tied to obesity, which affects nearly 30% of the state’s adults. Reducing kidney failure incidence requires sustained investment in managing these chronic conditions at the population level. At the same time, expanding living and deceased donor transplant programs — which cost Medicare approximately $64,000 less per patient per year than dialysis — would simultaneously improve patient outcomes and reduce long-term healthcare costs across the state.
Sources:
- Kidney Transplant Centers in Connecticut
- Kidney failure in Connecticut: 2026
- Kidney failure in Connecticut: 2025
- Kidney failure in Connecticut: 2024
- Kidney failure in Connecticut: 2023
- Kidney failure in Connecticut: 2022
- Kidney failure (ESRD) – in Connecticut
- Explore Chronic Kidney Disease in Connecticut | AHR
- Kidney Disease Mortality | Stats of the States | CDC
- Connecticut — Chronic Kidney Disease (CKD) State Fact Sheet
- Death Rate Report for Connecticut by County Kidney & Renal Pelvis, 2019-2023
- Incidence Rate Report for Connecticut by County Kidney & Renal Pelvis (Late Stage), 2018-2022
- Quick Profiles: Connecticut
- Cancer in Connecticut
- Incidence Rate Report for Connecticut by County Kidney & Renal Pelvis (All Stages), 2018-2022
- Connecticut Kidney Care: A National Overview
- Kidney Disease (Nephritis & Nephrosis) Death Rates Table for Connecticut by County